


Haemochromatosis and Erectile Dysfunction
Learn how iron overload affects erections and explore treatment options with a UK pharmacist-led consultation.
Takes less than 2 minutes to complete 100% online
Treatment Options
Pricing Disclaimer: Prices on some pages may not be up to date — the live pricing table below and pricing shown during consultation are official current prices and take precedence over any other figures on the site.




Haemochromatosis and Erectile Dysfunction: Understanding the Link and Treatment Options
Published: 14 October 2026
Haemochromatosis and erectile dysfunction are closely connected, as excess iron deposits can damage the pituitary gland and testes, disrupting hormone production essential for normal erections. This hereditary condition causes the body to absorb too much iron from food, leading to iron overload that affects multiple organs including those involved in sexual function. Understanding this link is important because treating the underlying iron overload alongside managing ED symptoms can significantly improve quality of life for men with haemochromatosis.
Key takeaways
- Haemochromatosis causes ED by damaging the pituitary gland and testes, reducing testosterone production.
- Treating iron overload through venesection is essential and may improve erectile function over time.
- Oral PDE5 inhibitors can help manage ED symptoms even when hormonal damage persists.
- Liver cirrhosis and diabetes from haemochromatosis require careful prescribing and dose adjustments.
- Lifestyle changes like exercise, stopping smoking, and limiting alcohol support both conditions.
How Haemochromatosis Causes Erectile Dysfunction
Haemochromatosis leads to erectile dysfunction through several interconnected mechanisms. The excess iron accumulates in the pituitary gland, which controls the production of luteinising hormone (LH) and follicle-stimulating hormone (FSH). These hormones signal the testes to produce testosterone, so when the pituitary is damaged by iron deposits, testosterone levels often fall significantly. Low testosterone is a well-established cause of reduced libido and difficulty achieving or maintaining erections.
Iron can also deposit directly in the testes, damaging the cells that produce testosterone and affecting the tissue responsible for sperm production. Additionally, haemochromatosis frequently causes liver cirrhosis and diabetes, both of which independently increase the risk of erectile dysfunction. Liver disease alters hormone metabolism, whilst diabetes damages the blood vessels and nerves essential for normal erectile function. The combination of hormonal disruption, vascular damage, and metabolic changes makes ED particularly common in men with untreated or poorly controlled haemochromatosis.
Assessing Erectile Dysfunction in Men with Haemochromatosis
If you have haemochromatosis and are experiencing erectile difficulties, a thorough assessment is essential to identify all contributing factors. Your GP or specialist will typically check your serum ferritin and transferrin saturation levels to assess how well your iron overload is controlled. Blood tests for testosterone, LH, FSH, and prolactin help determine whether pituitary or testicular damage is affecting your hormone levels. Fasting glucose and HbA1c tests screen for diabetes, whilst liver function tests assess any hepatic involvement.
A detailed medical history will explore the onset and pattern of your erectile difficulties, your current haemochromatosis treatment (such as venesection frequency), other medications, and cardiovascular risk factors. Because ED can be an early warning sign of heart disease, your doctor may assess your blood pressure, cholesterol, and overall cardiovascular health [1]. It is important to discuss all your current medicines, as some treatments for complications of haemochromatosis—such as diuretics or beta-blockers for heart problems—can themselves contribute to erectile dysfunction. This comprehensive approach ensures that both the underlying iron overload and any secondary causes of ED are properly addressed.
The Importance of Treating the Underlying Condition
Managing haemochromatosis effectively through regular venesection (blood removal) or chelation therapy is the foundation of treatment. Reducing iron levels can sometimes improve pituitary and testicular function, particularly if treatment begins before irreversible damage occurs. However, if hypogonadism (low testosterone) persists despite good iron control, testosterone replacement therapy may be considered under specialist supervision. Addressing associated conditions such as diabetes and liver disease is equally important, as better metabolic control can improve erectile function independently of iron levels.
At a glance
Lifestyle Measures for Haemochromatosis and Erectile Dysfunction
Lifestyle changes play a valuable supporting role in managing erectile dysfunction when you have haemochromatosis. Maintaining a healthy weight reduces the risk of diabetes and cardiovascular disease, both of which worsen ED. Regular physical activity improves blood flow, helps control blood sugar, and can boost testosterone levels naturally. Aim for at least 150 minutes of moderate-intensity exercise each week, such as brisk walking, cycling, or swimming.
Limiting alcohol is particularly important for men with haemochromatosis, as alcohol can worsen liver damage and directly impair erectile function. Heavy drinking also interferes with testosterone production and can reduce the effectiveness of ED treatments. Smoking damages blood vessels throughout the body, including those supplying the penis, so stopping smoking is one of the most effective steps you can take to improve erections. A balanced diet that supports liver health and stable blood sugar—rich in vegetables, whole grains, lean protein, and healthy fats—benefits both your haemochromatosis management and sexual health. Reducing stress through relaxation techniques, adequate sleep, and open communication with your partner can also help, as anxiety and relationship strain often compound physical causes of ED.
Oral ED Treatments for Men with Haemochromatosis
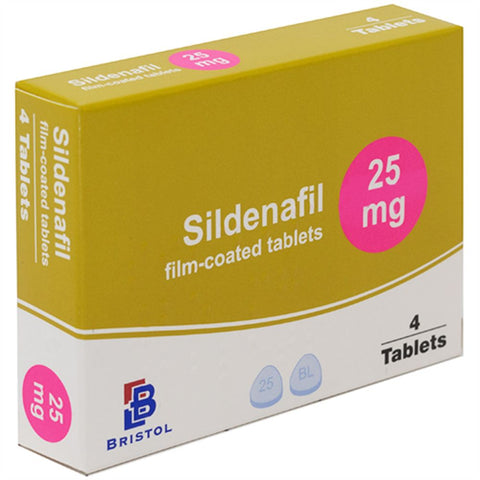
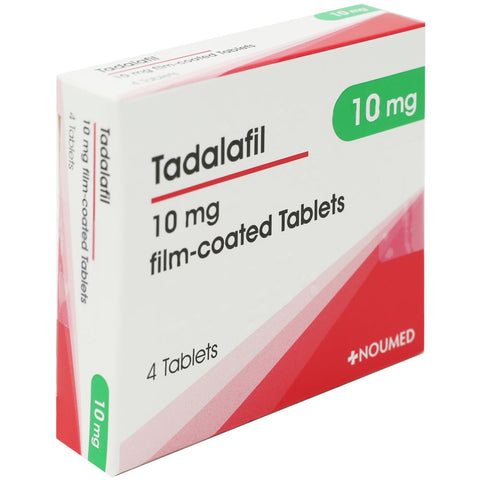
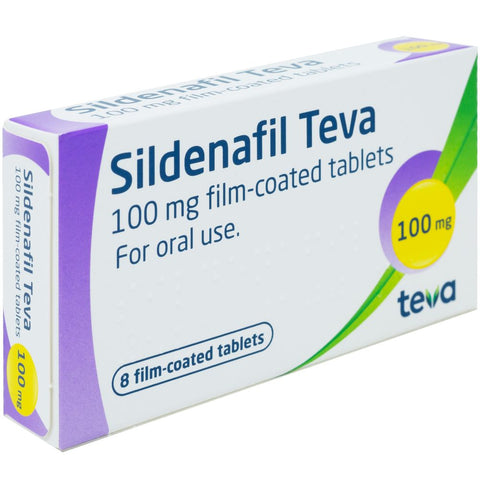
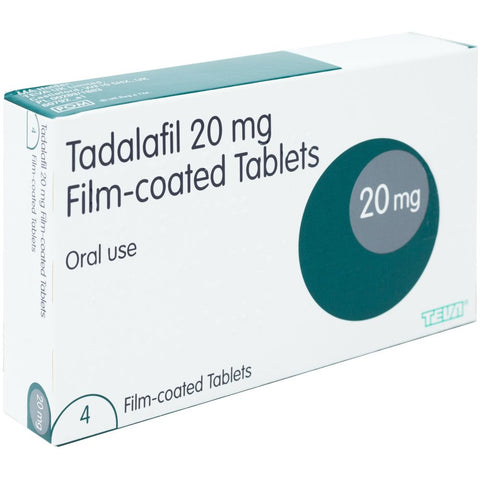
Oral medicines called PDE5 inhibitors are the first-line treatment for erectile dysfunction in men with haemochromatosis, provided there are no contraindications [2]. These medicines—sildenafil (Viagra), tadalafil (Cialis), vardenafil (Levitra), and avanafil (Spedra)—work by increasing blood flow to the penis in response to sexual stimulation. They do not cure ED or address the underlying hormonal or vascular damage caused by iron overload, but they can help you achieve and maintain an erection sufficient for sexual activity.
Sildenafil is usually taken about one hour before sex at doses of 25mg, 50mg, or 100mg, with effects lasting around four to six hours [3]. Tadalafil can be taken on-demand (10mg or 20mg at least 30 minutes before sex, with effects lasting up to 36 hours) or as a daily low dose (2.5mg or 5mg), which allows for more spontaneity [4]. Vardenafil (5mg, 10mg, or 20mg) is taken 25 to 60 minutes before sex [5], whilst avanafil (50mg, 100mg, or 200mg) works within 15 to 30 minutes [6]. All require sexual stimulation to work and should be taken no more than once in 24 hours. Your prescriber will recommend the most suitable option based on your individual circumstances, other medications, and how well your haemochromatosis and any complications are controlled.
Starting Treatment Safely
Before prescribing a PDE5 inhibitor, your doctor or pharmacist will review your full medical history and current medicines. Men with haemochromatosis often have additional health conditions—such as diabetes, liver disease, or heart problems—that require careful consideration. PDE5 inhibitors are generally well tolerated, but they must never be taken with nitrates (such as GTN spray or isosorbide mononitrate), nicorandil, riociguat, or recreational drugs called poppers, as this combination can cause a dangerous drop in blood pressure. If you take alpha-blockers for prostate symptoms or blood pressure, you will usually start on the lowest dose of a PDE5 inhibitor to minimise the risk of dizziness. Your prescriber will check every current medicine during the consultation to ensure safety.
Optimise Your Iron Control First
Regular venesection to reduce iron overload is the foundation of managing haemochromatosis and may improve erectile function over time. Work with your specialist to achieve target ferritin levels, then consider oral ED treatment if symptoms persist.
Treatment Cautions Specific to Haemochromatosis and Erectile Dysfunction
Men with haemochromatosis may have liver cirrhosis, which can affect how the body processes medicines. Severe liver impairment may require dose adjustments or mean that certain PDE5 inhibitors are not suitable; your prescriber will assess your liver function and choose the safest option. If you have developed heart failure or cardiomyopathy as a complication of iron overload, your doctor will need to confirm that sexual activity is safe for you before prescribing ED treatment, as PDE5 inhibitors are not recommended when physical exertion poses a risk.
Diabetes is common in haemochromatosis and can cause nerve damage (neuropathy) and blood vessel disease, both of which reduce the effectiveness of oral ED medicines. Whilst PDE5 inhibitors can still help, response rates may be lower, and you may need a higher dose or a trial of different options to find what works best. If you are taking medicines that interact with PDE5 inhibitors—such as certain antifungals, antibiotics, or HIV treatments—your prescriber will adjust the dose or choose an alternative. Always declare all your current medicines, including over-the-counter products and supplements, during your consultation. If testosterone replacement is being considered for persistent hypogonadism, this will be managed by a specialist, as it requires careful monitoring and is not suitable for everyone.
Getting Help for Haemochromatosis and Erectile Dysfunction at Cured Pharmacy
Cured Pharmacy is a GPhC-registered online pharmacy (GPhC 9012511) offering discreet access to licensed ED treatments following a clinical consultation with a UK-registered prescriber. If you have haemochromatosis and are experiencing erectile difficulties, you can complete a confidential online health questionnaire that asks about your iron overload management, current medicines, complications such as diabetes or liver disease, and cardiovascular health. A UK prescriber will review your answers to ensure that an oral ED treatment is safe and appropriate for you.
We stock a range of PDE5 inhibitors at transparent prices, including generic and branded options to suit different budgets and preferences. All medicines are dispensed by our qualified pharmacists and delivered in plain, unmarked packaging. If your consultation identifies any concerns—such as uncontrolled diabetes, significant liver impairment, or a medicine interaction—the prescriber may recommend that you see your GP or specialist before starting ED treatment. We encourage you to discuss your erectile difficulties with your haemochromatosis care team, as optimising your iron control and managing complications can improve your response to ED medicines. Erectile dysfunction is common in men with haemochromatosis, and effective treatments are available to help restore your confidence and quality of life.
When to See Your GP
You should see your GP if you develop new or worsening erectile difficulties, as this may indicate that your haemochromatosis or associated conditions need better control. Your doctor can check your iron levels, hormone profile, blood sugar, and liver function, and refer you to a specialist if needed. If you experience chest pain during sex, an erection lasting more than four hours, or sudden loss of vision or hearing after taking an ED medicine, seek urgent medical help. Regular follow-up with your haemochromatosis care team is essential to monitor your overall health and adjust treatment as needed.
When to get urgent help
- Erection lasting more than 4 hours (priapism) – go to A&E immediately
- Sudden loss of vision or hearing after taking ED medicine – seek urgent medical help
- Chest pain during or after sexual activity – call 999
- Severe dizziness or fainting after taking ED treatment – seek same-day medical advice
- New or worsening erectile difficulties with unexplained weight loss or fatigue – see your GP promptly to check haemochromatosis control
Call 999 or go to A&E in an emergency, or contact NHS 111 for urgent advice.
Scientific References
- NHS. (n.d.). Erectile dysfunction (impotence). NHS website. https://www.nhs.uk/conditions/erection-problems-erectile-dysfunction/ [accessed 14 October 2026]
- National Institute for Health and Care Excellence. (n.d.). Erectile dysfunction. Clinical Knowledge Summaries. https://cks.nice.org.uk/topics/erectile-dysfunction/ [accessed 14 October 2026]
- Joint Formulary Committee. (n.d.). Sildenafil. British National Formulary. NICE. https://bnf.nice.org.uk/drugs/sildenafil/ [accessed 14 October 2026]
- Joint Formulary Committee. (n.d.). Tadalafil. British National Formulary. NICE. https://bnf.nice.org.uk/drugs/tadalafil/ [accessed 14 October 2026]
- Joint Formulary Committee. (n.d.). Vardenafil. British National Formulary. NICE. https://bnf.nice.org.uk/drugs/vardenafil/ [accessed 14 October 2026]
- Joint Formulary Committee. (n.d.). Avanafil. British National Formulary. NICE. https://bnf.nice.org.uk/drugs/avanafil/ [accessed 14 October 2026]
Information on this page is for educational purposes only and is not medical advice. Prescription treatments require clinical assessment by a UK-registered prescriber. Always consult a qualified healthcare professional before starting or changing any medication.
Trusted by thousands
Real people, real results
“Fabulous service and quick delivery”
“Felt the effects of these after about 5 days. Erections are better and can get aroused and ready easier”
“Excellent value and brilliant customer service”
“I received excellent service and everything went well. The order arrived quickly and in perfect condition. It's working very well! Thank you to the whole team for the great work!”
“Delivery was good, the product lived up to expectations.”
Your Path to Treatment


Ready to Speak to a Pharmacist?
Reviewed by UK-based prescribers · Takes under 3 minutes · Discreet Packaging
Frequently Asked Questions
Can't find your answer? Our UK pharmacists review every consultation and can help.
Can haemochromatosis cause permanent erectile dysfunction?
Haemochromatosis can cause lasting erectile dysfunction if iron deposits permanently damage the pituitary gland or testes, leading to irreversible hypogonadism. However, early diagnosis and effective iron control through venesection can prevent or limit this damage, and oral ED treatments can help manage symptoms even when hormonal changes persist.
Will treating my haemochromatosis cure my erectile dysfunction?
Reducing iron levels through regular venesection or chelation therapy may improve erectile function, particularly if treatment starts before significant organ damage occurs. However, if pituitary or testicular damage has already caused permanent hypogonadism, ED may persist and require additional treatment such as PDE5 inhibitors or, in some cases, specialist-supervised testosterone replacement.
Are PDE5 inhibitors safe if I have liver cirrhosis from haemochromatosis?
PDE5 inhibitors can be used in mild to moderate liver impairment, but severe cirrhosis may require dose adjustments or mean certain options are not suitable. Your prescriber will assess your liver function during the consultation and choose the safest medicine and dose for your individual circumstances.
Can I take ED medicines if I have diabetes caused by haemochromatosis?
Yes, PDE5 inhibitors are commonly prescribed for men with diabetes, including diabetes secondary to haemochromatosis. However, nerve and blood vessel damage from diabetes can reduce the effectiveness of these medicines, so you may need to try different options or doses to find what works best for you.
Will testosterone replacement help my erectile dysfunction if I have haemochromatosis?
If blood tests confirm persistent low testosterone (hypogonadism) despite good iron control, testosterone replacement may be considered under specialist supervision. It can improve libido and energy, and may help erectile function, but it is not suitable for everyone and requires careful monitoring for side effects and contraindications.
How quickly do oral ED medicines work for men with haemochromatosis?
Sildenafil works in about one hour, tadalafil in at least 30 minutes (on-demand dosing), vardenafil in 25–60 minutes, and avanafil in 15–30 minutes. Response times are similar to men without haemochromatosis, though effectiveness may be lower if you have significant nerve damage, blood vessel disease, or very low testosterone.
Can I use ED treatment if I take medicines for heart problems caused by haemochromatosis?
It depends on the specific medicines you take. PDE5 inhibitors must never be used with nitrates, nicorandil, or riociguat due to the risk of dangerous low blood pressure. If you take alpha-blockers, you will usually start on the lowest dose of a PDE5 inhibitor. Your prescriber will review all your current medicines during the consultation to ensure safety.
Should I see my GP before using an online pharmacy for ED treatment if I have haemochromatosis?
It is a good idea to discuss erectile difficulties with your GP or haemochromatosis specialist, as they can check your iron levels, hormone profile, and overall health. An online consultation with a UK prescriber can then assess whether an oral ED treatment is safe and suitable, but if there are concerns about uncontrolled complications or complex interactions, you may be advised to see your doctor first.

Medically reviewed by
Tarun Kumar, Superintendent Pharmacist (GPhC 2233073)