

Penile Rehabilitation After Prostatectomy
Learn how early treatment may support erectile recovery after prostate surgery, with UK pharmacist-led consultations available.
Takes less than 2 minutes to complete 100% online
Penile Rehabilitation After Prostatectomy: Restoring Erectile Function
Published: 15 October 2026
Penile rehabilitation after prostatectomy is a structured approach to help restore erectile function following prostate surgery, particularly radical prostatectomy for prostate cancer. Many men experience erectile dysfunction (ED) after the procedure due to temporary or permanent nerve damage, but early intervention with medications, devices, or other therapies may improve the chances of recovery. This page explains how penile rehabilitation works, who may benefit, and the treatment options available through UK pharmacies and the NHS.
Key takeaways
- Penile rehabilitation after prostatectomy aims to preserve tissue health and support erectile recovery through early intervention.
- PDE5 inhibitors, vacuum devices, and injections are common options; choice depends on nerve preservation and individual circumstances.
- Recovery can take 12 to 24 months; not all men regain full function, but early treatment may improve outcomes.
- Lifestyle measures like stopping smoking and managing diabetes support vascular health and complement medical treatments.
- Treatments require a UK prescriber consultation to ensure safety and check for interactions with other medicines.
What is penile rehabilitation after prostatectomy?
Penile rehabilitation after prostatectomy refers to the early and regular use of treatments designed to encourage blood flow to the penis and support the recovery of erectile function after prostate surgery [1][2]. Radical prostatectomy, often performed to treat localised prostate cancer, can damage or disturb the delicate nerves and blood vessels responsible for erections, even when nerve-sparing techniques are used [8].
The goal of penile rehabilitation is not simply to achieve erections for sexual activity immediately after surgery, but to preserve penile tissue health and maximise the potential for natural erectile function to return over time. Without regular oxygenated blood flow, the smooth muscle tissue in the penis can undergo fibrosis (scarring), which may make future erections more difficult [8].
Rehabilitation programmes typically begin soon after surgery—often within a few weeks—and may involve oral medications (PDE5 inhibitors), vacuum erection devices, or intracavernosal injections. The approach is tailored to each individual, taking into account the type of surgery, nerve preservation, and personal preferences. While not every man will regain full erectile function, evidence suggests that early intervention may improve outcomes compared to waiting for spontaneous recovery [8].
How does penile rehabilitation work after prostate surgery?
Penile rehabilitation works by promoting regular blood flow to the penis, which helps maintain the health of erectile tissue during the recovery period [2][8]. After radical prostatectomy, the nerves that trigger erections may be bruised, stretched, or partially damaged. Even with nerve-sparing surgery, it can take many months—sometimes up to two years—for nerve function to recover.
During this time, spontaneous erections (including nocturnal erections) are often absent, meaning the penis receives less oxygen-rich blood than usual. This lack of oxygenation can lead to smooth muscle atrophy and fibrosis, potentially reducing the ability to achieve erections in the future [8]. Rehabilitation aims to counteract this by artificially inducing erections or increasing penile blood flow on a regular basis.
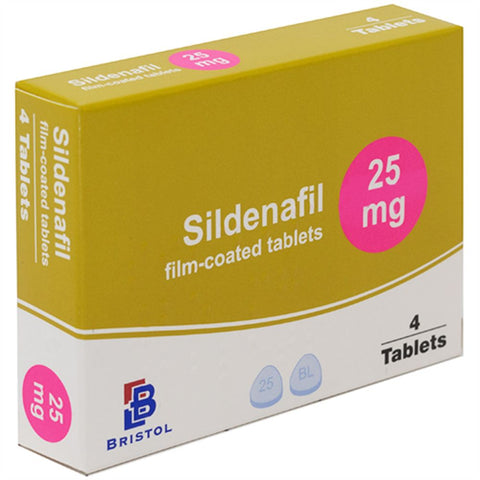
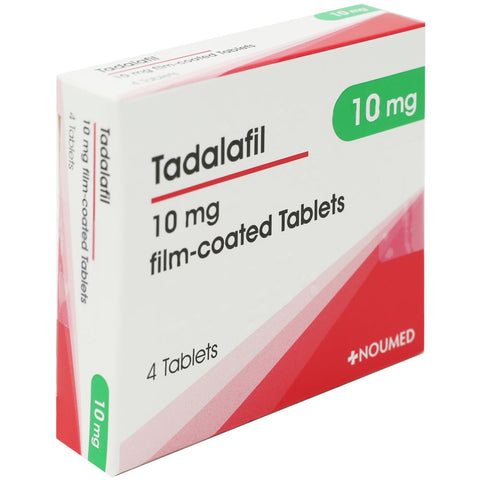
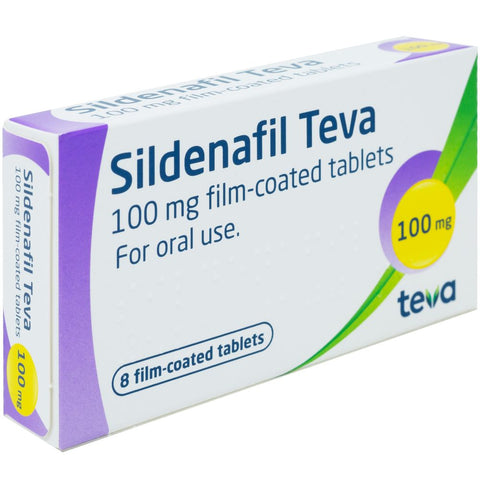
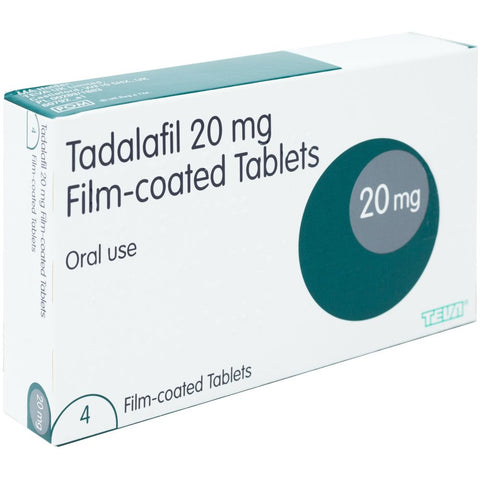
Common methods include PDE5 inhibitors such as sildenafil, tadalafil, vardenafil, or avanafil, which enhance blood flow when sexual stimulation occurs [3][4][5][6]. Some clinicians recommend daily low-dose tadalafil to provide continuous support. Vacuum erection devices create negative pressure to draw blood into the penis, and can be used regularly even without sexual activity. Intracavernosal injections of alprostadil directly stimulate an erection and are sometimes used in more intensive rehabilitation protocols [7]. The choice of treatment depends on individual circumstances, tolerability, and the advice of the surgical or urology team.
PDE5 inhibitors in penile rehabilitation
PDE5 inhibitors are the most commonly used oral medications in penile rehabilitation programmes after prostatectomy [2][8]. These medicines—sildenafil (Viagra), tadalafil (Cialis), vardenafil (Levitra), and avanafil (Spedra)—work by relaxing smooth muscle in the blood vessels of the penis, allowing increased blood flow in response to sexual stimulation [3][4][5][6]. They do not cause automatic erections; arousal is still required.
In the context of rehabilitation, PDE5 inhibitors may be prescribed on-demand (taken before anticipated sexual activity) or as a daily regimen, particularly with low-dose tadalafil (2.5 mg or 5 mg daily). The daily approach is thought to provide a steady level of the drug, supporting regular blood flow and potentially aiding tissue recovery [4]. Clinical trials have shown that early use of PDE5 inhibitors after nerve-sparing prostatectomy may improve the return of spontaneous erections, though results vary and not all men will regain full function [8][9].
It is important to start PDE5 inhibitors only when medically appropriate—usually once the surgical catheter is removed and healing is underway—and under the guidance of a urologist or GP. Side effects can include headache, flushing, indigestion, and nasal congestion, and these medicines are not suitable for men taking nitrates or certain other medications [3][4][5][6]. A UK-registered prescriber will review your medical history and current medicines during an online or in-person consultation before prescribing.
Who may benefit from penile rehabilitation after prostatectomy?
Penile rehabilitation may be most beneficial for men who have undergone nerve-sparing radical prostatectomy and wish to maximise their chances of recovering erectile function [2][8]. Younger men, those with good erectile function before surgery, and those with bilateral (both sides) nerve preservation tend to have better outcomes, though older men and those with unilateral nerve sparing may also benefit to some degree.
Men who are motivated to engage with a structured rehabilitation programme—whether using daily medication, regular vacuum device sessions, or injections—are more likely to see improvements. It is also important that the individual is medically fit to use the chosen treatment; for example, PDE5 inhibitors are not suitable for men taking nitrates for angina or those with certain cardiovascular conditions [3][4][5][6].
Not every man will regain natural erections sufficient for penetrative sex, even with rehabilitation. Factors such as the extent of nerve damage, pre-existing vascular health, diabetes, smoking, and age all influence recovery [1][2]. However, many men find that early intervention helps preserve penile length, improves the quality of any returning erections, and provides psychological reassurance during a challenging recovery period. It is essential to have realistic expectations and to discuss goals openly with your urology team or GP.
Effectiveness of penile rehabilitation programmes
The effectiveness of penile rehabilitation after prostatectomy varies widely between individuals and depends on several factors, including the type of surgery, nerve preservation, baseline erectile function, and adherence to the rehabilitation protocol [8]. Some studies suggest that early use of PDE5 inhibitors or vacuum devices can improve the rate and quality of erectile function recovery compared to no treatment, though the evidence is not unanimous and further research is ongoing [8][9].
In clinical trials of PDE5 inhibitors after nerve-sparing prostatectomy, a proportion of men regained erections sufficient for intercourse, particularly when treatment was started early and used regularly [9]. Daily low-dose tadalafil has been investigated specifically for penile rehabilitation, with some trials showing modest improvements in spontaneous erectile function over time [4]. Vacuum erection devices have also been shown to help maintain penile length and support blood flow, though they require regular use and some men find them cumbersome.
It is important to understand that penile rehabilitation is not a guarantee of full recovery. Some men will experience significant improvement, some will see partial benefit, and others may not regain natural erections despite treatment. The process can take many months, and patience is essential. Combining medical treatments with lifestyle measures—such as stopping smoking, managing diabetes and blood pressure, maintaining a healthy weight, and staying physically active—can further support vascular health and improve overall outcomes [1][2].
Timeframe for recovery
Recovery of erectile function after prostatectomy is a gradual process, and the timeframe varies considerably. Nerve regeneration can take anywhere from several months to two years, and some degree of function may continue to improve even beyond that period [2][8]. Early return of morning or spontaneous erections is often a positive sign that nerve recovery is underway.
Penile rehabilitation programmes typically recommend starting treatment within the first few weeks to three months after surgery, once initial healing has occurred and the catheter has been removed. Regular use of PDE5 inhibitors, vacuum devices, or injections is then continued for at least 12 to 24 months, with periodic review by the urology team. Some men may need to continue treatment long-term if natural function does not fully return, using on-demand PDE5 inhibitors or other aids to achieve erections for sexual activity.
Setting realistic expectations and maintaining open communication with your healthcare team is crucial. Many men find it helpful to track progress, celebrate small improvements, and seek psychological support if the emotional impact of ED becomes difficult to manage. Penile rehabilitation is as much about preserving hope and quality of life as it is about physical recovery.
Start early for best results
Beginning penile rehabilitation within the first few months after surgery, under your urology team's guidance, may maximise your chances of recovering erectile function and preserving penile tissue health.
Side effects and safety considerations
PDE5 inhibitors used in penile rehabilitation after prostatectomy are generally well tolerated, but side effects can occur [3][4][5][6]. Common side effects include headache, facial flushing, indigestion, nasal congestion, and back pain (particularly with tadalafil). These are usually mild and often lessen with continued use. Rarely, men may experience visual disturbances such as a blue tinge to vision (more common with sildenafil) or sudden hearing loss; if this happens, stop the medication and seek medical advice promptly.
PDE5 inhibitors must never be taken with nitrates (such as GTN spray or isosorbide mononitrate), nicorandil, riociguat, or recreational drugs known as 'poppers', as the combination can cause a dangerous drop in blood pressure [3][4][5][6]. Men taking alpha-blockers for urinary symptoms (common after prostate surgery) should start on the lowest dose of PDE5 inhibitor and be stable on the alpha-blocker first, as both types of medicine can lower blood pressure. Your prescriber will check for these interactions during the consultation.
Vacuum erection devices are non-invasive and have few side effects, though some men experience bruising, numbness, or discomfort, especially if the constriction ring is left on too long (it should not be worn for more than 30 minutes). Intracavernosal injections carry a small risk of priapism (a prolonged, painful erection lasting more than four hours), which requires urgent medical treatment to prevent permanent damage [7]. If you experience an erection lasting more than four hours, go to A&E immediately. Always follow the instructions provided by your healthcare team and report any concerns.
Comparing penile rehabilitation options with oral ED tablets
Oral PDE5 inhibitor tablets—such as sildenafil, tadalafil, vardenafil, and avanafil—are a cornerstone of penile rehabilitation after prostatectomy, but they are not the only option [2][8]. Vacuum erection devices, intracavernosal injections (alprostadil), and intraurethral alprostadil (Vitaros) offer alternatives for men who cannot use or do not respond to tablets [7]. Each approach has different mechanisms, advantages, and practical considerations.
PDE5 inhibitor tablets are convenient, taken by mouth, and work by enhancing the body's natural erectile response to sexual stimulation [3][4][5][6]. They are effective for many men after nerve-sparing surgery, particularly when started early, but they require some degree of nerve function to work optimally. In the early months after prostatectomy, when nerves are still recovering, response to tablets may be limited, and higher doses or combination with other methods may be needed.
Vacuum devices work mechanically, drawing blood into the penis regardless of nerve function, making them useful even when nerve damage is severe. They can be used daily for rehabilitation or on-demand for sexual activity, and they do not involve systemic medication, so there are no drug interactions. However, they require manual dexterity, can feel awkward, and some men find the erections less natural. Intracavernosal injections produce reliable erections independently of nerve function and are highly effective, but they involve self-injection into the penis, which some men find daunting, and carry a small risk of priapism [7]. The choice of treatment should be guided by your urology team, taking into account your surgical outcome, lifestyle, and personal preferences.
NHS availability and private options
Penile rehabilitation treatments, including PDE5 inhibitors, are sometimes available on NHS prescription following prostatectomy, particularly in the first year after surgery, though policies vary by local integrated care board (ICB) [2]. Your urologist or GP can advise on NHS eligibility and may provide an initial supply or ongoing prescriptions if criteria are met. Vacuum erection devices may also be available on the NHS for post-prostatectomy rehabilitation.
If NHS provision is limited or you prefer the convenience of an online service, UK-registered online pharmacies such as Cured Pharmacy offer private prescriptions for PDE5 inhibitors following a clinical consultation with a UK prescriber. This can be a practical option for ongoing treatment once the initial rehabilitation phase is established. All prescription medicines require a consultation to ensure they are safe and appropriate for you, taking into account your medical history, current medications, and recovery progress.
It is important to continue working with your urology team or GP even if you obtain private prescriptions, as they can monitor your overall recovery, adjust treatment as needed, and provide support for any complications or concerns. Penile rehabilitation is most successful when it is part of a coordinated care plan, with regular follow-up and open communication between you and your healthcare providers.
When to get urgent help
- Erection lasting more than 4 hours (priapism) – go to A&E immediately to prevent permanent damage
- Sudden loss of vision or hearing while using PDE5 inhibitors – stop the medication and seek urgent medical advice
- Chest pain during or after sexual activity – call 999; do not take further doses of ED medication
- Severe allergic reaction (swelling of face, lips, tongue, or difficulty breathing) – call 999 immediately
Call 999 or go to A&E in an emergency, or contact NHS 111 for urgent advice.
Scientific References
- NHS. (n.d.). Erectile dysfunction (impotence). NHS website. https://www.nhs.uk/conditions/erection-problems-erectile-dysfunction/ [accessed 15 October 2026]
- National Institute for Health and Care Excellence. (n.d.). Erectile dysfunction. Clinical Knowledge Summaries. https://cks.nice.org.uk/topics/erectile-dysfunction/ [accessed 15 October 2026]
- Joint Formulary Committee. (n.d.). Sildenafil. British National Formulary. NICE. https://bnf.nice.org.uk/drugs/sildenafil/ [accessed 15 October 2026]
- Joint Formulary Committee. (n.d.). Tadalafil. British National Formulary. NICE. https://bnf.nice.org.uk/drugs/tadalafil/ [accessed 15 October 2026]
- Joint Formulary Committee. (n.d.). Vardenafil. British National Formulary. NICE. https://bnf.nice.org.uk/drugs/vardenafil/ [accessed 15 October 2026]
- Joint Formulary Committee. (n.d.). Avanafil. British National Formulary. NICE. https://bnf.nice.org.uk/drugs/avanafil/ [accessed 15 October 2026]
- Joint Formulary Committee. (n.d.). Alprostadil. British National Formulary. NICE. https://bnf.nice.org.uk/drugs/alprostadil/ [accessed 15 October 2026]
- European Association of Urology. (n.d.). EAU Guidelines on Sexual and Reproductive Health. https://uroweb.org/guidelines/sexual-and-reproductive-health [accessed 15 October 2026]
- Goldstein, I., Lue, T. F., Padma-Nathan, H., Rosen, R. C., Steers, W. D., & Wicker, P. A. (1998). Oral sildenafil in the treatment of erectile dysfunction. New England Journal of Medicine, 338(20), 1397–1404. https://pubmed.ncbi.nlm.nih.gov/9580646/ [accessed 15 October 2026]
Information on this page is for educational purposes only and is not medical advice. Prescription treatments require clinical assessment by a UK-registered prescriber. Always consult a qualified healthcare professional before starting or changing any medication.
Get Discreet ED Treatment Online
Reviewed by UK-based prescribers · Takes under 3 minutes · Discreet Packaging
ED Treatments We Offer
Pricing Disclaimer: Prices on some pages may not be up to date — the live pricing table below and pricing shown during consultation are official current prices and take precedence over any other figures on the site.




Trusted by thousands
Real people, real results
“Fabulous service and quick delivery”
“Felt the effects of these after about 5 days. Erections are better and can get aroused and ready easier”
“Excellent value and brilliant customer service”
“I received excellent service and everything went well. The order arrived quickly and in perfect condition. It's working very well! Thank you to the whole team for the great work!”
“Delivery was good, the product lived up to expectations.”
How Our Online Service Works
Choose your treatment
Select from our recommended UK-licensed medications.

Answer quick questions
Select safe UK treatments. Quick answers.

Get it delivered fast
We will deliver direct to you as quickly as tomorrow.

Your Questions Answered
Can't find your answer? Our UK pharmacists review every consultation and can help.
When should I start penile rehabilitation after prostatectomy?
Most urologists recommend starting penile rehabilitation within a few weeks to three months after surgery, once the catheter is removed and initial healing is complete. Early intervention may improve outcomes, but always follow your surgical team's specific advice.
Will penile rehabilitation guarantee that my erections return?
No treatment can guarantee full recovery of erectile function after prostatectomy. Rehabilitation may improve the chances and quality of recovery, but outcomes depend on nerve preservation, age, overall health, and individual factors.
Can I use PDE5 inhibitors like sildenafil or tadalafil immediately after prostate surgery?
You should only start PDE5 inhibitors when your urologist or GP advises it is safe, usually after the catheter is removed and healing is underway. A prescriber will assess your suitability and check for any contraindications or interactions with other medicines.
How long do I need to continue penile rehabilitation?
Rehabilitation programmes typically last 12 to 24 months, as nerve recovery can take up to two years. Some men may need ongoing treatment if natural function does not fully return, using on-demand PDE5 inhibitors or other aids for sexual activity.
Are vacuum erection devices effective for penile rehabilitation after prostatectomy?
Yes, vacuum devices can be effective for maintaining penile blood flow and length during recovery, and they work independently of nerve function. Regular use may support tissue health, though some men find them less convenient than tablets.
Can I get penile rehabilitation treatments on the NHS?
PDE5 inhibitors and vacuum devices may be available on NHS prescription after prostatectomy, particularly in the first year, though policies vary by local area. Your urologist or GP can advise on NHS eligibility and prescribing options.
What should I do if I experience side effects from PDE5 inhibitors during rehabilitation?
Common side effects like headache or flushing are usually mild and may lessen over time. If you experience sudden vision or hearing loss, chest pain, or an erection lasting more than four hours, seek urgent medical help and stop the medication.
Can lifestyle changes help with penile rehabilitation after prostate surgery?
Yes, stopping smoking, managing diabetes and blood pressure, maintaining a healthy weight, and staying physically active all support vascular health and may improve erectile function recovery alongside medical treatments.

Medically reviewed by
Tarun Kumar, Superintendent Pharmacist (GPhC 2233073)