

Hormonal Erectile Dysfunction: Causes & Treatment
Understand how hormones affect erections and explore UK treatment options through a pharmacist-led consultation.
Takes less than 2 minutes to complete 100% online

Available Treatments
Pricing Disclaimer: Prices on some pages may not be up to date — the live pricing table below and pricing shown during consultation are official current prices and take precedence over any other figures on the site.
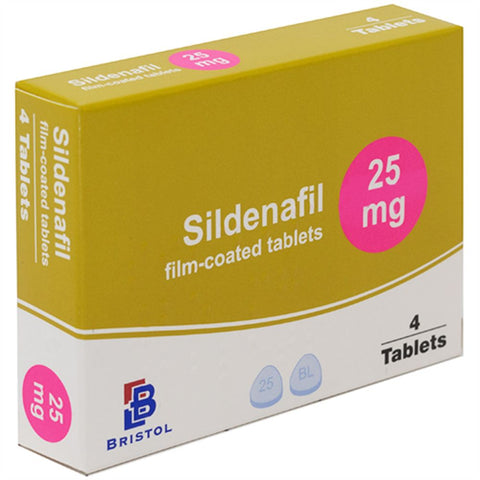
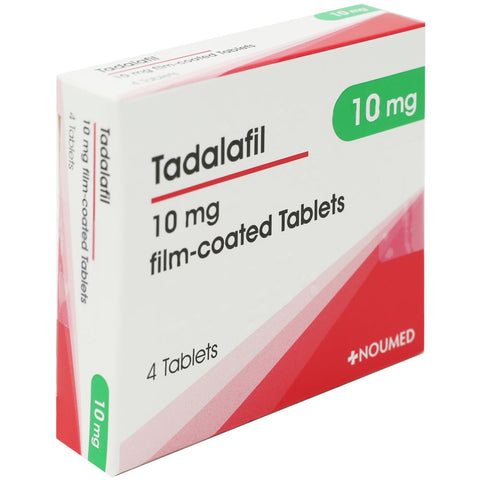
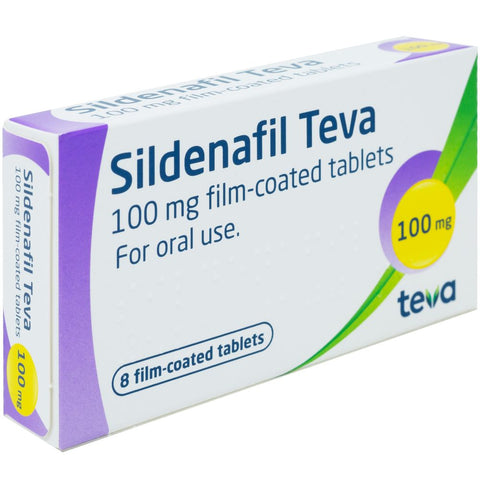
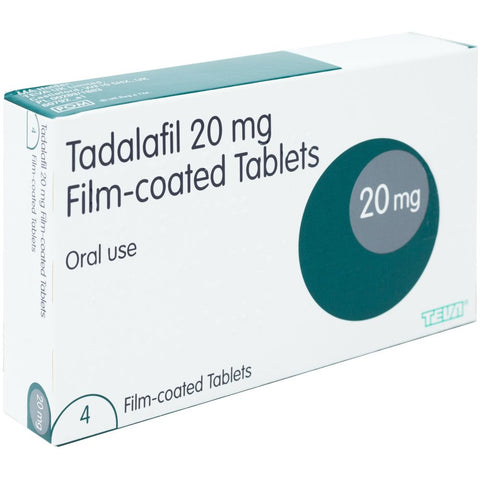




Trusted by thousands
Real people, real results
“Fabulous service and quick delivery”
“Felt the effects of these after about 5 days. Erections are better and can get aroused and ready easier”
“Excellent value and brilliant customer service”
“I received excellent service and everything went well. The order arrived quickly and in perfect condition. It's working very well! Thank you to the whole team for the great work!”
“Delivery was good, the product lived up to expectations.”
Get Treatment in 3 Steps
Choose your treatment
Select from our recommended UK-licensed medications.

Answer quick questions
Select safe UK treatments. Quick answers.

Get it delivered fast
We will deliver direct to you as quickly as tomorrow.

Hormonal Erectile Dysfunction: Causes, Diagnosis and Treatment
Published: 15 October 2026
Hormonal erectile dysfunction occurs when imbalances in hormones—particularly testosterone, thyroid hormones, or prolactin—interfere with the ability to achieve or maintain an erection. While hormones play an important role in sexual function, they account for a relatively small proportion of ED cases; most men with erectile difficulties have vascular, psychological, or medication-related causes. If you suspect a hormonal cause, a simple blood test arranged by your GP can identify imbalances, and treatment of the underlying hormone problem may improve erections alongside other proven therapies.
At a glance
What is hormonal erectile dysfunction?
Hormonal erectile dysfunction refers to erection problems caused or worsened by abnormal levels of hormones that regulate sexual desire, blood flow, and nerve signalling [1]. The most commonly implicated hormone is testosterone, which supports libido and the mechanisms that allow blood vessels in the penis to relax and fill. Low testosterone (hypogonadism) can reduce sexual interest and make erections less firm, though many men with low testosterone still achieve erections if their blood vessels and nerves are healthy.
Other hormones can also contribute. An underactive thyroid (hypothyroidism) slows metabolism and can dampen libido and erectile response, while an overactive thyroid (hyperthyroidism) may cause anxiety and circulatory changes that interfere with erections. Elevated prolactin—a hormone normally involved in milk production—can suppress testosterone and reduce sexual desire in men. High cortisol from chronic stress or Cushing's syndrome may also impair sexual function. Because these conditions often produce other symptoms (fatigue, weight changes, mood disturbances), your GP will consider the broader clinical picture when investigating hormonal erectile dysfunction [2].
How do hormones affect erections?
An erection depends on a coordinated sequence: sexual arousal triggers nerve signals that relax smooth muscle in the penile arteries, allowing blood to flow in and compress the veins so blood is temporarily trapped. Testosterone supports this process by maintaining the health of the endothelial cells lining blood vessels, preserving nitric oxide production (the key chemical messenger for vessel relaxation), and sustaining libido. Men with very low testosterone may notice reduced spontaneous erections (such as morning erections) and diminished interest in sex, though the ability to respond to direct stimulation often remains if vascular health is intact [1][2].
Thyroid hormones regulate metabolic rate and cardiovascular function. Hypothyroidism can lead to sluggish circulation, reduced energy, and lower libido, all of which may contribute to erectile difficulties. Hyperthyroidism can increase heart rate and anxiety, sometimes making it harder to relax enough for an erection. Prolactin, when elevated, inhibits the release of gonadotropin-releasing hormone, which in turn lowers testosterone. The result is often reduced sexual desire and weaker erections. Cortisol, the stress hormone, can interfere with testosterone production and contribute to performance anxiety, creating a cycle that worsens erectile function over time.
Common hormonal causes of erectile dysfunction
Low testosterone is the most frequent hormonal cause of ED, particularly in older men, though levels decline gradually with age and many men retain normal function. Hypogonadism can be primary (testicular failure) or secondary (pituitary or hypothalamic disorders). Symptoms beyond ED include reduced muscle mass, increased body fat, low mood, fatigue, and loss of body hair. Blood tests measuring total and free testosterone, ideally taken in the morning when levels peak, confirm the diagnosis [2].
Thyroid disorders affect around 1 in 20 people in the UK, with hypothyroidism being more common. Men with an underactive thyroid may experience weight gain, cold intolerance, constipation, and erectile difficulties. Hyperthyroidism can cause weight loss, heat intolerance, palpitations, and anxiety-related ED. Elevated prolactin (hyperprolactinaemia) may result from a benign pituitary tumour (prolactinoma), certain medications (especially some antipsychotics and anti-sickness drugs), or kidney disease. Symptoms include reduced libido, erectile dysfunction, and occasionally breast enlargement or nipple discharge. Diabetes, obesity, and metabolic syndrome can also disrupt hormone balance, creating a complex interplay between vascular and hormonal factors in erectile dysfunction [1][2].
When to suspect a hormonal cause
Consider a hormonal cause if you have lost interest in sex (low libido) alongside erection problems, if you have noticed other symptoms such as unexplained fatigue, mood changes, weight gain or loss, or if you have a known condition affecting your pituitary, thyroid, or testes. Hormonal ED often develops gradually rather than suddenly, and morning erections may become less frequent. Your GP will take a full history, examine you, and arrange blood tests to measure testosterone, prolactin, thyroid-stimulating hormone (TSH), and sometimes luteinising hormone (LH) and follicle-stimulating hormone (FSH) to pinpoint the underlying problem [2].
What you need to know
- Hormonal erectile dysfunction is often caused by low testosterone, thyroid disorders, or high prolactin.
- Blood tests arranged by your GP can identify hormone imbalances and guide treatment.
- PDE5 inhibitors work effectively even with low testosterone and are available after an online consultation.
- Treating the underlying hormone problem may improve erections, often alongside ED medication.
- ED can signal heart disease or diabetes, so see your GP if you have new or worsening symptoms.
Diagnosing hormonal erectile dysfunction
Diagnosis begins with a consultation with your GP, who will ask about the onset and pattern of your erection difficulties, your libido, general health, medications, and lifestyle. A physical examination may check for signs of hormone imbalance such as reduced body hair, breast tissue development (gynaecomastia), or testicular abnormalities. Blood tests are essential: a morning sample for total testosterone is the first step, and if low, a repeat test plus measurement of sex hormone-binding globulin (SHBG), LH, FSH, and prolactin helps distinguish primary from secondary hypogonadism [2].
Thyroid function tests (TSH and free thyroxine) identify thyroid disorders, and a fasting glucose or HbA1c may be checked to screen for diabetes, which commonly coexists with ED. If prolactin is elevated, an MRI scan of the pituitary gland may be arranged to look for a prolactinoma. It is important to remember that most men with ED have normal hormone levels; vascular disease (often linked to smoking, high blood pressure, high cholesterol, or diabetes) is a far more common cause. Your GP may also assess cardiovascular risk, as ED can be an early warning sign of heart disease [1][2].
What happens if a hormone problem is found?
If blood tests confirm low testosterone and you have symptoms, your GP or an endocrinologist may offer testosterone replacement therapy (TRT), available as gels, injections, or patches. TRT can improve libido, energy, and mood, and may help erections, though it does not work immediately and benefits vary. If the cause is a pituitary problem, treating that condition (for example, with medication or surgery for a prolactinoma) may restore normal testosterone. Thyroid disorders are managed with levothyroxine for hypothyroidism or antithyroid drugs for hyperthyroidism, and correcting thyroid levels often improves sexual function. Even when hormone treatment is started, many men benefit from PDE5 inhibitors (such as sildenafil or tadalafil) to directly support the erection mechanism while hormones normalise [2].
Treatment options for hormonal erectile dysfunction
Treating the underlying hormone imbalance is the first priority, but this may take weeks or months to show full benefit. In the meantime, or if hormone correction alone does not fully restore erections, PDE5 inhibitor tablets are highly effective and work regardless of whether ED has a hormonal, vascular, or psychological cause [1][2]. These medicines—sildenafil (Viagra), tadalafil (Cialis), vardenafil (Levitra), and avanafil (Spedra)—enhance the natural erection process by increasing blood flow to the penis when you are sexually aroused. They do not affect hormone levels but provide reliable support for achieving and maintaining an erection.
Sildenafil is taken about one hour before sex and works for around four hours; tadalafil can be taken on-demand (effect lasting up to 36 hours) or as a low daily dose for spontaneity; vardenafil acts within 25–60 minutes; and avanafil works in as little as 15–30 minutes [3][4][5][6]. All require sexual stimulation to work and are available on prescription after a consultation. Lifestyle changes—maintaining a healthy weight, exercising regularly, limiting alcohol, stopping smoking, and managing stress—support both hormone health and vascular function. If you are on testosterone replacement, your doctor will monitor your response and check that your red blood cell count and prostate remain healthy. Combining hormone treatment with a PDE5 inhibitor often gives the best results for men with confirmed hormonal erectile dysfunction [2].
When to get urgent help
- Erection lasting more than 4 hours (priapism) – go to A&E immediately
- Sudden loss of vision or hearing – stop the medicine and seek urgent medical help
- Chest pain during sex – stop, rest, and call 999 if pain does not settle quickly
- Severe dizziness or fainting after taking ED medicine – contact 111 or your GP urgently
Call 999 or go to A&E in an emergency, or contact NHS 111 for urgent advice.
Getting help and next steps
If you are experiencing erectile difficulties, especially if accompanied by low libido, fatigue, or other symptoms, book an appointment with your GP. They can arrange the necessary blood tests and refer you to a specialist if needed. Do not delay: ED can be an early sign of diabetes or cardiovascular disease, and early intervention improves outcomes [1]. If a hormone problem is identified and treated, or if your tests are normal, you can access effective ED treatment through Cured Pharmacy's online consultation service.
Our UK-registered prescribers review your medical history and current medications to ensure safe, suitable treatment. We offer a range of PDE5 inhibitors, including affordable generic options such as sildenafil from £0.45 per tablet (£0.36 with first-order code Ednew) and tadalafil from £7.95 (£6.36 with code Ednew), as well as branded Viagra and Cialis. Prescriptions are dispensed by our GPhC-registered pharmacy and delivered discreetly to your door. Remember, treating hormonal erectile dysfunction is a partnership between you, your GP, and, where appropriate, an online pharmacy service that provides convenient access to proven medications once the diagnosis is clear [2].
When to seek urgent help
Seek immediate medical attention if you develop an erection lasting more than four hours (priapism), sudden loss of vision or hearing, or chest pain during sexual activity. These are rare but serious side effects of ED treatment that require emergency care. If you experience severe headache, dizziness, or fainting after taking an ED medicine, stop and contact 111 or your GP urgently. Always disclose all your current medications during your consultation, as some combinations—particularly with nitrates, nicorandil, or riociguat—are dangerous and must be avoided [3][4].
See your GP first
If you suspect low testosterone or another hormone problem, ask your GP for blood tests before starting ED treatment. Once a diagnosis is clear, PDE5 inhibitors can be prescribed online and delivered discreetly.
Scientific References
- NHS. (n.d.). Erectile dysfunction (impotence). NHS website. https://www.nhs.uk/conditions/erection-problems-erectile-dysfunction/ [accessed 15 October 2026]
- National Institute for Health and Care Excellence. (n.d.). Erectile dysfunction. Clinical Knowledge Summaries. https://cks.nice.org.uk/topics/erectile-dysfunction/ [accessed 15 October 2026]
- Joint Formulary Committee. (n.d.). Sildenafil. British National Formulary. NICE. https://bnf.nice.org.uk/drugs/sildenafil/ [accessed 15 October 2026]
- Joint Formulary Committee. (n.d.). Tadalafil. British National Formulary. NICE. https://bnf.nice.org.uk/drugs/tadalafil/ [accessed 15 October 2026]
- Joint Formulary Committee. (n.d.). Vardenafil. British National Formulary. NICE. https://bnf.nice.org.uk/drugs/vardenafil/ [accessed 15 October 2026]
- Joint Formulary Committee. (n.d.). Avanafil. British National Formulary. NICE. https://bnf.nice.org.uk/drugs/avanafil/ [accessed 15 October 2026]
Information on this page is for educational purposes only and is not medical advice. Prescription treatments require clinical assessment by a UK-registered prescriber. Always consult a qualified healthcare professional before starting or changing any medication.
Common Questions
Can low testosterone cause erectile dysfunction?
Yes, low testosterone can reduce libido and contribute to erectile difficulties, though many men with low testosterone still achieve erections if their blood vessels are healthy. Blood tests and treatment with testosterone replacement may help.
Will testosterone replacement cure my erectile dysfunction?
Testosterone replacement can improve libido, energy, and sometimes erections if your levels are low and symptomatic, but it does not work for everyone and may take weeks to show benefit. Many men also benefit from PDE5 inhibitors alongside hormone treatment.
How do I know if my ED is caused by hormones?
Hormonal ED often comes with low sexual desire, fatigue, mood changes, or other symptoms. Your GP can arrange blood tests for testosterone, thyroid hormones, and prolactin to confirm or rule out a hormonal cause.
Can thyroid problems cause erection difficulties?
Yes, both an underactive thyroid (hypothyroidism) and an overactive thyroid (hyperthyroidism) can affect libido, energy, and erectile function. Treating the thyroid disorder often improves sexual health.
Do PDE5 inhibitors work if I have low testosterone?
Yes, PDE5 inhibitors such as sildenafil and tadalafil work effectively even if you have low testosterone, because they act directly on blood vessels in the penis. Combining them with testosterone treatment (if needed) often gives the best results.
What blood tests will my GP do for hormonal erectile dysfunction?
Your GP will typically check morning testosterone, sex hormone-binding globulin, LH, FSH, prolactin, and thyroid-stimulating hormone (TSH). Fasting glucose or HbA1c may also be tested to screen for diabetes.
Can stress hormones cause erectile dysfunction?
Yes, chronic stress raises cortisol, which can lower testosterone and contribute to performance anxiety. Managing stress through lifestyle changes, exercise, or counselling can improve both hormone balance and erectile function.
Is hormonal erectile dysfunction permanent?
Not usually. If the underlying hormone imbalance is identified and treated—whether with testosterone replacement, thyroid medication, or treatment for high prolactin—erectile function often improves. PDE5 inhibitors provide additional support during and after treatment.
Take the First Step Today
Start your journey to better health today.
- Reviewed by UK-based prescribers
- Takes under 3 minutes
- Discreet Packaging
Start Your Journey To Better Health Today
Once you complete a short online assessment you will be able to choose your preferred treatment from safe medically approved options tailored to you.
Start My Assessment Log in to Your Account
Medically reviewed by
Tarun Kumar, Superintendent Pharmacist (GPhC 2233073)