


Erectile Dysfunction in Trans Women: Causes & Treatment
Understand how hormone therapy affects erections and explore safe, effective treatment options through our UK pharmacist-led service.
Takes less than 2 minutes to complete 100% online
Trusted by thousands
Real people, real results
“Fabulous service and quick delivery”
“Felt the effects of these after about 5 days. Erections are better and can get aroused and ready easier”
“Excellent value and brilliant customer service”
“I received excellent service and everything went well. The order arrived quickly and in perfect condition. It's working very well! Thank you to the whole team for the great work!”
“Delivery was good, the product lived up to expectations.”
Your Path to Treatment


Erectile Dysfunction in Trans Women: Causes, Treatment and Support
Published: 17 October 2026
Erectile dysfunction in trans women is a common experience, particularly for those taking feminising hormone therapy (oestrogen and anti-androgens), which can reduce spontaneous erections and affect erectile function. Many trans women welcome this change as part of gender-affirming care, while others may wish to preserve erectile function for sexual activity or future surgical options. Understanding the causes and available treatments can help you make informed choices that align with your health goals and gender journey.
At a glance
Why Does Erectile Dysfunction Occur in Trans Women?
Erectile dysfunction in trans women most commonly results from feminising hormone therapy. Oestrogen and anti-androgens (such as cyproterone acetate, spironolactone, or GnRH analogues) suppress testosterone, the hormone primarily responsible for spontaneous erections and libido. Lower testosterone levels reduce the frequency and firmness of erections, and many trans women notice this change within weeks to months of starting hormone therapy [1].
This effect is often a desired outcome of gender-affirming treatment, helping to reduce gender dysphoria. However, some trans women may wish to maintain erectile function for sexual intimacy, personal comfort, or to preserve penile tissue elasticity before potential gender-affirming surgery. Psychological factors—including stress, anxiety, depression, or body image concerns—can also contribute to erectile difficulties, as can underlying health conditions such as diabetes, cardiovascular disease, or the effects of smoking and alcohol [2].
It is important to remember that erectile function does not define sexual pleasure or intimacy. Many trans women explore different forms of sexual expression that feel affirming and satisfying, regardless of erectile capacity.
How Hormone Therapy Affects Erectile Function in Trans Women
Feminising hormone therapy deliberately lowers testosterone to levels typical of cisgender women, usually below 2 nmol/L. This reduction decreases the blood flow and nerve signals that trigger erections, and the smooth muscle tissue in the penis may become less responsive over time. The degree of erectile dysfunction varies: some trans women lose all spontaneous and stimulated erections, while others retain some function, especially with direct stimulation [1].
The type and dose of anti-androgen can influence the extent of erectile changes. Cyproterone acetate and GnRH analogues tend to suppress testosterone more completely than spironolactone, which may allow some residual erectile function. Oestrogen alone, without an anti-androgen, typically has a milder effect on erections but still reduces testosterone over time.
If you wish to preserve erectile function while on hormone therapy, discuss this openly with your gender clinic or prescribing clinician. Adjusting medication regimens, using the lowest effective anti-androgen dose, or taking planned breaks (under medical supervision) may help, though these approaches must be carefully balanced against your overall gender-affirming goals and health.
Can You Reverse Erectile Dysfunction After Stopping Hormones?
Erectile function may partially or fully return if hormone therapy is paused or stopped, though this depends on how long you have been on treatment and individual factors. Tissue changes can become more permanent over time, so early intervention—such as regular use of erections (spontaneous, through stimulation, or with medication)—may help maintain penile health. Always consult your gender specialist or GP before making any changes to your hormone regimen, as stopping or reducing hormones can affect your mental health and gender dysphoria.
Treatment Options for Erectile Dysfunction in Trans Women
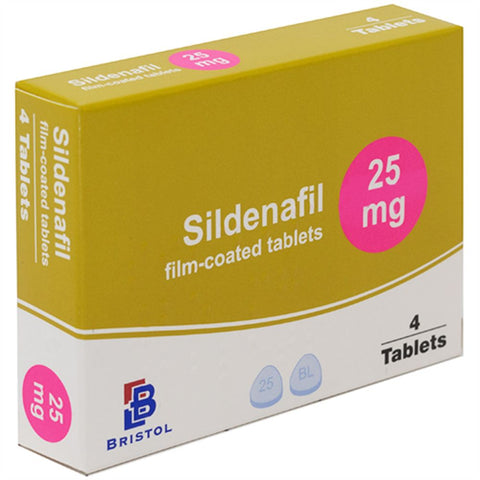
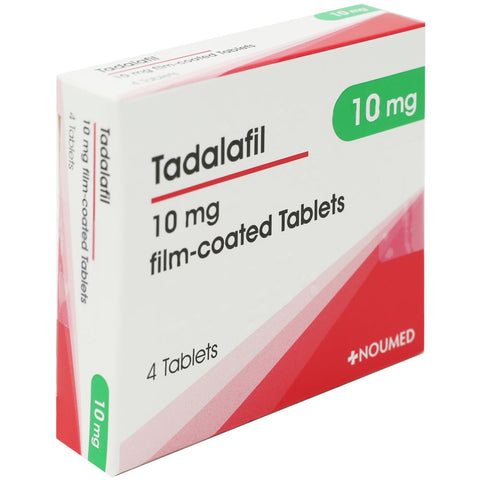
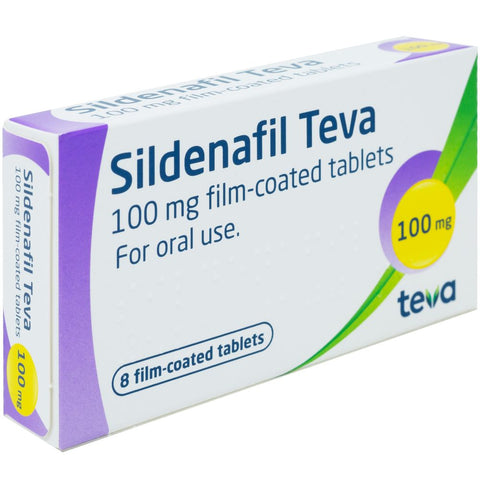
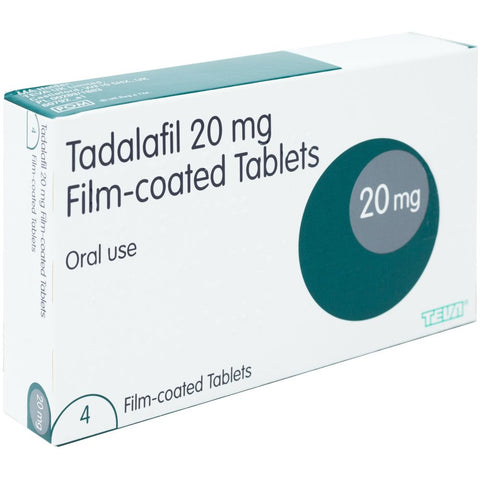
If you wish to achieve erections for sexual activity or to maintain penile tissue health, PDE5 inhibitor medications—such as sildenafil (Viagra), tadalafil (Cialis), vardenafil (Levitra), and avanafil (Spedra)—can be effective, even while continuing feminising hormone therapy. These medicines work by increasing blood flow to the penis in response to sexual stimulation; they do not cause spontaneous erections and require physical or mental arousal to work [3][4][5][6].
PDE5 inhibitors are prescription-only medicines in the UK. At Cured Pharmacy, a UK-registered prescriber reviews your online consultation to ensure the treatment is safe and suitable for you, taking into account your hormone therapy, any other medications, and your overall health. Sildenafil is taken about one hour before sex, tadalafil can be taken on-demand (effective for up to 36 hours) or daily at a lower dose, vardenafil works in 25–60 minutes, and avanafil is the fastest-acting, often effective within 15–30 minutes [3][4][5][6].
Other options include topical treatments (Eroxon gel, available without prescription, or prescription Vitaros alprostadil cream) and injectable alprostadil (Caverject). Vacuum erection devices are also available. Your choice depends on your preferences, lifestyle, and how your body responds. A healthcare professional can help you find the most suitable option.
What you need to know
- Feminising hormone therapy commonly causes erectile dysfunction by lowering testosterone levels
- PDE5 inhibitors like sildenafil and tadalafil can help achieve erections even while on hormones
- No major interaction between feminising hormones and PDE5 inhibitors is commonly reported
- Discuss your goals openly with your gender clinic to balance erectile function with gender-affirming care
- Lifestyle changes—stopping smoking, moderating alcohol, staying active—support better erectile health
Are PDE5 Inhibitors Safe for Trans Women on Hormone Therapy?
PDE5 inhibitors are generally safe for trans women taking oestrogen and anti-androgens, and no major drug interaction between feminising hormones and sildenafil, tadalafil, vardenafil, or avanafil is commonly reported. However, safety depends on your full medical history and all current medications, which is why a prescriber reviews your consultation before approving treatment [3][4][5][6].
You must never take a PDE5 inhibitor if you use nitrates (GTN spray, isosorbide mononitrate or dinitrate), nicorandil, riociguat, or recreational drugs known as 'poppers' (amyl or alkyl nitrites), because the combination can cause a dangerous drop in blood pressure. If you take an alpha-blocker (such as doxazosin or tamsulosin), you should be stable on that medicine and start on the lowest PDE5 dose. Medicines that strongly inhibit the liver enzyme CYP3A4—including some HIV antiretrovirals (ritonavir, cobicistat, Paxlovid), antifungals (ketoconazole, itraconazole), and antibiotics (clarithromycin)—can raise PDE5 inhibitor levels, requiring dose adjustments or avoidance [3][4][5][6].
Always declare every medicine, supplement, and recreational substance you use during your consultation. The prescriber will check for interactions and advise on the safest option and dose for you.
What About Spironolactone and Other Anti-Androgens?
Spironolactone, cyproterone acetate, and GnRH analogues do not have direct dangerous interactions with PDE5 inhibitors. Spironolactone can lower blood pressure, so combining it with a PDE5 inhibitor may increase the risk of dizziness or light-headedness, especially when standing up. This is usually manageable by starting on a low dose and monitoring how you feel. Your prescriber will review your full medication list to ensure safe use.
Practical Steps to Manage Erectile Dysfunction in Trans Women
If you want to maintain or regain erectile function, start by having an open conversation with your gender clinic, GP, or sexual health service. Explain your goals—whether for sexual activity, relationship intimacy, or preserving tissue for potential surgery—so they can tailor advice to your needs. Regular erections (whether through sexual activity, masturbation, or medication) may help maintain penile tissue health, though evidence specific to trans women is limited [2].
Lifestyle factors also matter. Smoking damages blood vessels and worsens erectile dysfunction; stopping smoking can improve vascular health. Heavy alcohol use impairs erectile function and interacts with PDE5 inhibitors, so moderation is advised. Regular physical activity, a balanced diet, and managing conditions like diabetes or high blood pressure all support better sexual health [1][2].
If you choose to try a PDE5 inhibitor, give it a fair trial: these medicines require sexual stimulation to work, and it may take several attempts to find the right dose and timing. If one medicine does not work well, another may suit you better. Mental and emotional well-being are equally important—consider speaking to a therapist experienced in LGBTQ+ health if anxiety, dysphoria, or relationship concerns are affecting your sexual confidence.
When to get urgent help
- Erection lasting more than 4 hours (priapism)—call 999 or go to A&E immediately
- Sudden loss of vision or hearing after taking ED medication—seek emergency medical help
- Chest pain during or after sexual activity—stop and call 999
- Severe dizziness, fainting, or rapid heartbeat after taking ED treatment—seek urgent medical advice
Call 999 or go to A&E in an emergency, or contact NHS 111 for urgent advice.
When to Speak to a Healthcare Professional About Erectile Dysfunction in Trans Women
You should speak to a GP, gender clinic, or sexual health specialist if erectile dysfunction is causing you distress, affecting your relationships, or if you wish to explore treatment options. Even if you are content with reduced erectile function, a healthcare conversation can clarify what to expect and ensure your overall health is monitored. Erectile dysfunction can sometimes signal underlying conditions such as cardiovascular disease or diabetes, so a general health check is worthwhile, especially if you have other symptoms like chest pain, breathlessness, or unexplained fatigue [1][2].
Seek urgent medical help (call 999 or go to A&E) if you experience an erection lasting more than four hours (priapism), sudden loss of vision or hearing, or chest pain during sexual activity. These are rare but serious side effects that require immediate attention [3][4].
At Cured Pharmacy, our online consultation is reviewed by a UK-registered prescriber who will assess whether a PDE5 inhibitor is safe and appropriate for you, considering your hormone therapy, other medications, and medical history. If treatment is approved, your medicine is dispensed by our GPhC-registered pharmacy and delivered discreetly to your door. If a PDE5 inhibitor is not suitable, the prescriber will explain why and may suggest alternative options or recommend you see your GP for further investigation.
What If PDE5 Inhibitors Do Not Work?
If oral PDE5 inhibitors are ineffective, other options include alprostadil cream (Vitaros, applied to the tip of the penis) or alprostadil injections (Caverject, injected into the side of the penis), both of which work independently of testosterone levels. Vacuum erection devices are non-drug alternatives. A specialist in sexual medicine or urology can discuss these with you and provide training if needed [7].
Preserve Function While on Hormones
If you wish to maintain erectile function during feminising hormone therapy, discuss this with your gender clinic early. Regular erections—through activity, stimulation, or PDE5 inhibitors—may help preserve penile tissue health and keep your options open for the future.
Scientific References
- NHS. (n.d.). Erectile dysfunction (impotence). NHS website. https://www.nhs.uk/conditions/erection-problems-erectile-dysfunction/ [accessed 17 October 2026]
- National Institute for Health and Care Excellence. (n.d.). Erectile dysfunction. Clinical Knowledge Summaries. https://cks.nice.org.uk/topics/erectile-dysfunction/ [accessed 17 October 2026]
- Joint Formulary Committee. (n.d.). Sildenafil. British National Formulary. NICE. https://bnf.nice.org.uk/drugs/sildenafil/ [accessed 17 October 2026]
- Joint Formulary Committee. (n.d.). Tadalafil. British National Formulary. NICE. https://bnf.nice.org.uk/drugs/tadalafil/ [accessed 17 October 2026]
- Joint Formulary Committee. (n.d.). Vardenafil. British National Formulary. NICE. https://bnf.nice.org.uk/drugs/vardenafil/ [accessed 17 October 2026]
- Joint Formulary Committee. (n.d.). Avanafil. British National Formulary. NICE. https://bnf.nice.org.uk/drugs/avanafil/ [accessed 17 October 2026]
- Joint Formulary Committee. (n.d.). Alprostadil. British National Formulary. NICE. https://bnf.nice.org.uk/drugs/alprostadil/ [accessed 17 October 2026]
Information on this page is for educational purposes only and is not medical advice. Prescription treatments require clinical assessment by a UK-registered prescriber. Always consult a qualified healthcare professional before starting or changing any medication.
Treatment Options
Pricing Disclaimer: Prices on some pages may not be up to date — the live pricing table below and pricing shown during consultation are official current prices and take precedence over any other figures on the site.




Ready to Speak to a Pharmacist?
Reviewed by UK-based prescribers · Takes under 3 minutes · Discreet Packaging
Frequently Asked Questions
Can trans women on oestrogen still get erections?
Yes, though hormone therapy reduces testosterone and makes spontaneous erections less frequent or firm. Many trans women can still achieve erections with direct stimulation or PDE5 inhibitor medication.
Will taking sildenafil or tadalafil interfere with my hormone therapy?
No major interaction between PDE5 inhibitors and feminising hormones (oestrogen, anti-androgens) is commonly reported. A prescriber will review your full medication list to confirm safety.
Do I need to stop hormone therapy to use erectile dysfunction treatment?
No. PDE5 inhibitors can work while you continue feminising hormone therapy. Discuss your goals with your gender clinic to ensure your treatment plan supports your overall well-being.
How quickly does hormone therapy cause erectile dysfunction?
Changes often begin within weeks to months of starting oestrogen and anti-androgens, as testosterone levels fall. The extent and speed vary individually depending on medication type and dose.
Is erectile dysfunction permanent after years on hormone therapy?
Erectile function may partially return if hormones are paused, though prolonged therapy can lead to tissue changes. Regular erections (through activity or medication) may help maintain tissue health.
Can I buy erectile dysfunction treatment without a prescription in the UK?
Viagra Connect (sildenafil 50mg) and Cialis Together (tadalafil 10mg) are available from pharmacies after a consultation. Prescription-strength doses require a prescriber's approval, which Cured Pharmacy provides online.
What if I experience side effects from PDE5 inhibitors?
Common side effects include headache, flushing, and indigestion. These are usually mild. Stop the medicine and seek urgent help if you have chest pain, sudden vision or hearing loss, or an erection lasting over four hours.
Should I see my GP about erectile dysfunction even if I am happy without erections?
A general health check is still worthwhile, as erectile dysfunction can signal cardiovascular or metabolic conditions. Your GP can assess your overall health and support your gender-affirming care.

Medically reviewed by
Tarun Kumar, Superintendent Pharmacist (GPhC 2233073)