

Addison's Disease and Erectile Dysfunction Explained
Understand the link, safe treatment options, and how a UK pharmacist-led consultation can help.
Takes less than 2 minutes to complete 100% online

Addison's Disease and Erectile Dysfunction: Understanding the Link and Treatment Options
Published: 13 October 2026
Addison's disease and erectile dysfunction are connected through hormonal pathways that affect sexual function. Addison's disease, also known as primary adrenal insufficiency, occurs when the adrenal glands fail to produce sufficient cortisol and aldosterone, and this hormonal disruption can significantly impact erectile function. Understanding this relationship is essential for managing both conditions effectively and safely.
At a glance
What Is Addison's Disease and How Does It Affect Erectile Function?
Addison's disease is a rare but serious condition in which the adrenal glands, located above the kidneys, do not produce enough of the hormones cortisol and aldosterone. Cortisol helps regulate metabolism, blood pressure, and the body's response to stress, while aldosterone controls salt and water balance. When these hormones are deficient, multiple body systems are affected, including sexual function.
Men with Addison's disease often experience erectile dysfunction through several mechanisms. Low cortisol levels lead to chronic fatigue, weakness, and reduced energy—all of which diminish libido and sexual performance. Additionally, the adrenal glands produce small amounts of androgens (male sex hormones), and their deficiency can further reduce sexual desire and erectile quality. The condition also causes low blood pressure, which can impair blood flow to the penis, making it difficult to achieve or maintain an erection.
The psychological burden of living with a chronic illness like Addison's disease—including anxiety, depression, and stress about health—can compound erectile difficulties. Many men find that addressing the underlying hormonal imbalance through proper replacement therapy is the first step toward improving sexual function, though additional support may still be needed.
How Addison's Disease and Erectile Dysfunction Are Assessed
If you have Addison's disease and are experiencing erectile dysfunction, your GP or endocrinologist will take a comprehensive approach to assessment. They will review your current hormone replacement therapy—typically hydrocortisone or prednisolone for cortisol, and fludrocortisone for aldosterone—to ensure doses are optimised. Inadequate replacement can leave you fatigued and hypotensive, both of which worsen ED.
Blood tests are essential to check cortisol levels, electrolytes, blood glucose, and sometimes testosterone. While Addison's disease itself does not directly lower testosterone production from the testes, the chronic stress and illness can suppress the hypothalamic-pituitary-gonadal axis, leading to secondary hypogonadism in some men. If testosterone is low, your doctor may discuss testosterone replacement therapy as part of your overall hormone management.
Your clinician will also assess cardiovascular health, as low blood pressure is a hallmark of Addison's disease and can contribute to ED. They will review all your current medications, check for other contributing factors such as diabetes or thyroid disorders (which can coexist with Addison's disease), and discuss psychological factors. A thorough assessment ensures that any treatment for ED is safe and appropriate given your adrenal insufficiency.
The Role of Hormone Optimisation
Optimising your glucocorticoid and mineralocorticoid replacement is the foundation of managing erectile dysfunction in Addison's disease. If your cortisol replacement is too low, you may experience persistent fatigue, low blood pressure, and poor stress response—all of which impair sexual function. Conversely, excessive steroid doses can cause side effects such as weight gain, high blood pressure, and mood changes, which also affect sexual health. Working closely with your endocrinologist to fine-tune your hormone doses can lead to significant improvements in energy, well-being, and erectile function before any ED-specific treatment is considered.
Lifestyle Measures to Support Sexual Health with Addison's Disease
Lifestyle adjustments play an important role in managing both Addison's disease and erectile dysfunction. Adequate salt and fluid intake is crucial for people with Addison's disease to maintain blood pressure and prevent dehydration, both of which support better circulation and erectile function. Your doctor will advise on the right amount of salt for your individual needs.
Regular, moderate exercise can improve cardiovascular fitness, mood, and energy levels, all of which benefit sexual health. However, it is important to adjust your hydrocortisone dose on days of increased physical activity or stress, as advised by your endocrinologist, to avoid adrenal crisis and fatigue. Overexertion without adequate steroid cover can worsen ED symptoms.
Managing stress is particularly important, as physical or emotional stress can trigger adrenal insufficiency symptoms and worsen erectile problems. Techniques such as mindfulness, paced breathing, and good sleep hygiene can help. Limiting alcohol is advisable, as it can lower blood pressure further and interfere with sexual performance. Smoking cessation is strongly encouraged, as smoking damages blood vessels and significantly worsens erectile dysfunction. A balanced diet that supports stable blood sugar and overall health is also beneficial, especially if you have coexisting diabetes or other autoimmune conditions.
What you need to know
- Addison's disease can cause ED through low cortisol, fatigue, low blood pressure, and reduced libido.
- Optimising your steroid replacement therapy is the first step to improving sexual function.
- PDE5 inhibitors like sildenafil and tadalafil can be safe and effective if your condition is stable.
- Always declare all medicines during consultation; never use ED tablets with nitrates or poppers.
- See your GP if ED is new or worsening, as it may signal other health issues.
Treatment Options for Addison's Disease and Erectile Dysfunction
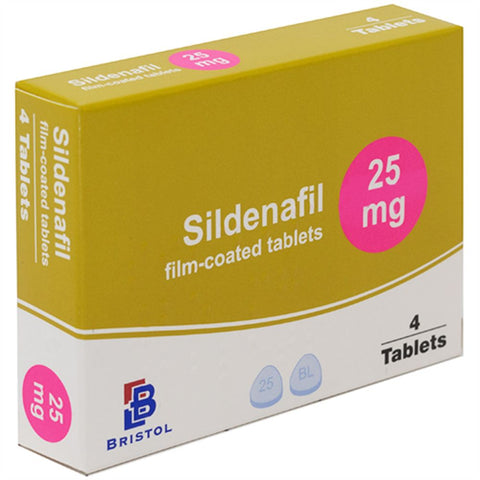
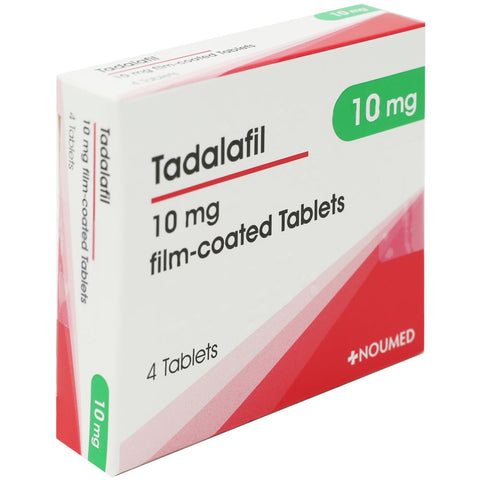
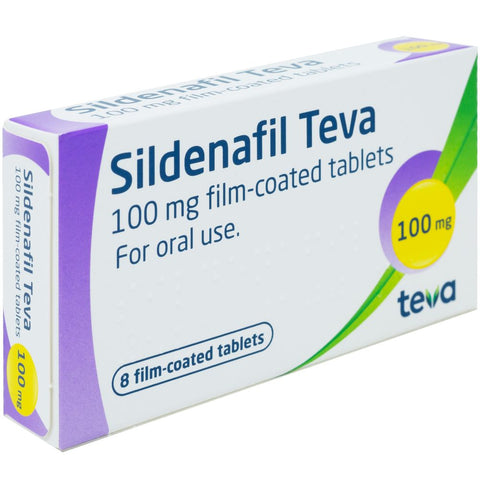
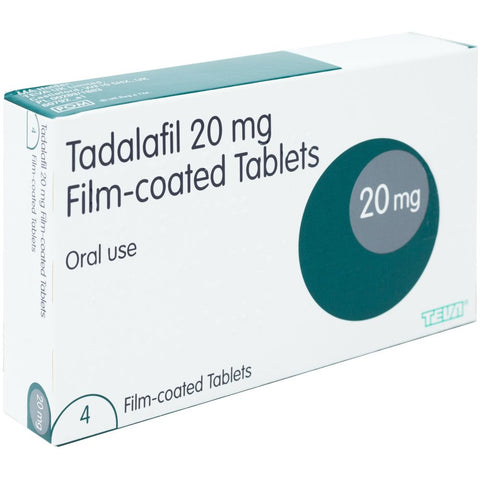
Once your hormone replacement therapy is optimised, oral PDE5 inhibitor medications are often effective for treating erectile dysfunction in men with Addison's disease. These medicines—sildenafil (Viagra), tadalafil (Cialis), vardenafil (Levitra), and avanafil (Spedra)—work by increasing blood flow to the penis during sexual stimulation. They do not cure ED but can help you achieve and maintain an erection sufficient for sexual activity [1][2].
Sildenafil is taken about one hour before sex and is effective for around four to six hours. Tadalafil can be taken on-demand (at least 30 minutes before sex, with effects lasting up to 36 hours) or as a lower daily dose for spontaneity. Vardenafil works within 25 to 60 minutes, and avanafil is the fastest-acting, often effective within 15 to 30 minutes. All require sexual arousal to work and are taken a maximum of once daily [3][4][5][6].
At Cured Pharmacy, these treatments are available following an online consultation reviewed by a UK-registered prescriber. The prescriber will check your Addison's disease is stable, review your current medications (especially any blood pressure medicines), and ensure a PDE5 inhibitor is safe for you. If oral tablets are not suitable or effective, your GP may discuss other options such as Vitaros (alprostadil cream) or Caverject (alprostadil injection), which work through different mechanisms [7].
Starting Treatment Safely
Because Addison's disease often involves low blood pressure, starting on the lowest effective dose of a PDE5 inhibitor is usually recommended. Your prescriber will assess your blood pressure control and ensure your steroid replacement is stable before prescribing. It is essential to declare all your current medications during the consultation, as some medicines can interact with ED treatments. Never take PDE5 inhibitors if you use nitrates (such as GTN spray), nicorandil, or recreational drugs called poppers, as the combination can cause a dangerous drop in blood pressure.
Important Safety Considerations and Drug Interactions
Men with Addison's disease must be particularly cautious about drug interactions and blood pressure effects when using ED treatments. PDE5 inhibitors can lower blood pressure, and because Addison's disease often causes low blood pressure already, this effect must be carefully managed. Your prescriber will check that your blood pressure is stable on your current hormone replacement before approving treatment.
Never take a PDE5 inhibitor if you are using nitrates (GTN spray, isosorbide mononitrate or dinitrate), nicorandil, riociguat, or recreational nitrites (poppers). This combination can cause a severe and potentially life-threatening drop in blood pressure. If you take alpha-blockers such as doxazosin or tamsulosin for prostate symptoms, you must be stable on that medicine and start ED treatment at the lowest dose, as the combination increases the risk of dizziness and fainting.
Some medications can affect how PDE5 inhibitors are broken down in the body. Potent CYP3A4 inhibitors (such as ritonavir, ketoconazole, itraconazole, or clarithromycin) can raise levels of ED medicines, requiring dose adjustments or avoidance depending on the specific drug. Conversely, CYP3A4 inducers like rifampicin or carbamazepine can reduce effectiveness. Grapefruit juice should be avoided. During your consultation, the prescriber or pharmacist will review every medicine you take to identify any interactions. Never stop or change a prescribed medicine without professional advice [3][4][5][6].
When ED Treatment May Not Be Suitable
PDE5 inhibitors are not suitable for everyone. They should not be used if sexual activity itself is inadvisable—for example, if you have recently had a heart attack or stroke, have unstable angina, or severe heart failure. They are also contraindicated if you have very low blood pressure, a history of sudden vision loss (non-arteritic anterior ischaemic optic neuropathy, or NAION), or certain inherited retinal disorders. Your prescriber will assess your full medical history to ensure treatment is safe for you [2][12].
When to get urgent help
- Erection lasting more than 4 hours (priapism) – go to A&E immediately
- Sudden loss of vision or hearing after taking ED medicine – seek urgent medical help
- Chest pain during or after sexual activity – call 999
- Severe weakness, confusion, vomiting, or collapse (possible adrenal crisis) – call 999
- Dizziness or fainting after taking ED treatment – stop and contact your GP or 111 same day
Call 999 or go to A&E in an emergency, or contact NHS 111 for urgent advice.
When to Seek Further Help and What to Expect
If you experience new or worsening erectile dysfunction, it is important to see your GP or endocrinologist, even if you already have Addison's disease. ED can sometimes signal other health issues such as cardiovascular disease, diabetes, or thyroid problems, which are more common in people with autoimmune conditions like Addison's disease. Early assessment ensures any additional problems are identified and managed.
If you are prescribed a PDE5 inhibitor and it does not work after several attempts, do not simply increase the dose yourself. Contact your prescriber to discuss the response. Sometimes a different medicine, a higher dose, or a review of your hormone replacement therapy is needed. If one PDE5 inhibitor does not suit you, another may work better, as individual responses vary.
Seek urgent medical help if you develop an erection lasting more than four hours (priapism), sudden loss of vision or hearing, or chest pain during sexual activity. These are rare but serious side effects requiring immediate attention. If you experience symptoms of an adrenal crisis—such as severe weakness, confusion, abdominal pain, vomiting, or collapse—call 999 immediately, as this is a medical emergency. Always carry your steroid emergency card and ensure those around you know about your Addison's disease [1][2][12].
Optimise Your Hormones First
Work closely with your endocrinologist to fine-tune your cortisol and aldosterone replacement before starting ED treatment. Stable hormone levels improve energy, blood pressure, and sexual function, making ED medicines more effective and safer.
Scientific References
- NHS. (n.d.). Erectile dysfunction (impotence). NHS website. https://www.nhs.uk/conditions/erection-problems-erectile-dysfunction/ [accessed 13 October 2026]
- National Institute for Health and Care Excellence. (n.d.). Erectile dysfunction. Clinical Knowledge Summaries. https://cks.nice.org.uk/topics/erectile-dysfunction/ [accessed 13 October 2026]
- Joint Formulary Committee. (n.d.). Sildenafil. British National Formulary. NICE. https://bnf.nice.org.uk/drugs/sildenafil/ [accessed 13 October 2026]
- Joint Formulary Committee. (n.d.). Tadalafil. British National Formulary. NICE. https://bnf.nice.org.uk/drugs/tadalafil/ [accessed 13 October 2026]
- Joint Formulary Committee. (n.d.). Vardenafil. British National Formulary. NICE. https://bnf.nice.org.uk/drugs/vardenafil/ [accessed 13 October 2026]
- Joint Formulary Committee. (n.d.). Avanafil. British National Formulary. NICE. https://bnf.nice.org.uk/drugs/avanafil/ [accessed 13 October 2026]
- Joint Formulary Committee. (n.d.). Alprostadil. British National Formulary. NICE. https://bnf.nice.org.uk/drugs/alprostadil/ [accessed 13 October 2026]
- Electronic Medicines Compendium. (n.d.). Summaries of Product Characteristics and Patient Information Leaflets. https://www.medicines.org.uk/emc/ [accessed 13 October 2026]
Information on this page is for educational purposes only and is not medical advice. Prescription treatments require clinical assessment by a UK-registered prescriber. Always consult a qualified healthcare professional before starting or changing any medication.
Treatment Options
Pricing Disclaimer: Prices on some pages may not be up to date — the live pricing table below and pricing shown during consultation are official current prices and take precedence over any other figures on the site.




Frequently Asked Questions
Can Addison's disease cause erectile dysfunction?
Yes, Addison's disease can cause erectile dysfunction through low cortisol and aldosterone levels, leading to fatigue, low blood pressure, reduced libido, and impaired blood flow to the penis.
Will treating my Addison's disease improve my erectile dysfunction?
Optimising your hormone replacement therapy often improves energy, blood pressure, and sexual function, but many men still benefit from additional ED treatment such as PDE5 inhibitors.
Are ED tablets safe if I have Addison's disease?
PDE5 inhibitors can be safe for men with Addison's disease if your condition is stable and your blood pressure is controlled, but a prescriber must review your full medical history and current medicines first.
Can I take sildenafil or tadalafil with my steroid replacement therapy?
Yes, there is no direct interaction between hydrocortisone, prednisolone, or fludrocortisone and PDE5 inhibitors, but your prescriber will check your blood pressure and overall health before prescribing.
What should I do if my blood pressure is very low?
If your blood pressure is very low, PDE5 inhibitors may not be suitable until your steroid doses are optimised and your blood pressure is stable. Discuss this with your endocrinologist or GP.
Can low testosterone from Addison's disease cause ED?
Addison's disease can reduce adrenal androgen production, and chronic illness may lower testosterone levels. If blood tests confirm low testosterone, your doctor may discuss testosterone replacement therapy.
How quickly will ED treatment work?
Sildenafil works in about one hour, tadalafil in 30 minutes to 2 hours, vardenafil in 25–60 minutes, and avanafil in 15–30 minutes. All require sexual stimulation to be effective.
What if ED tablets don't work for me?
If PDE5 inhibitors are not effective after several attempts, contact your prescriber to review your dose, try a different medicine, or discuss alternatives such as alprostadil cream or injections.
Trusted by thousands
Real people, real results
“Fabulous service and quick delivery”
“Felt the effects of these after about 5 days. Erections are better and can get aroused and ready easier”
“Excellent value and brilliant customer service”
“I received excellent service and everything went well. The order arrived quickly and in perfect condition. It's working very well! Thank you to the whole team for the great work!”
“Delivery was good, the product lived up to expectations.”
Your Path to Treatment
Choose your treatment
Select from our recommended UK-licensed medications.

Answer quick questions
Select safe UK treatments. Quick answers.

Get it delivered fast
We will deliver direct to you as quickly as tomorrow.

Ready to Speak to a Pharmacist?
Reviewed by UK-based prescribers · Takes under 3 minutes · Discreet Packaging

Medically reviewed by
Tarun Kumar, Superintendent Pharmacist (GPhC 2233073)